At the end of 2025, 4,723 CMPA members were anesthesiologists.
Graphic 1 compares the 10-year trends of anesthesiologists’ medico-legal experiences with those of all CMPA members.
What Are the Relative Risks of a Medico-Legal Case for Anesthesiologists?
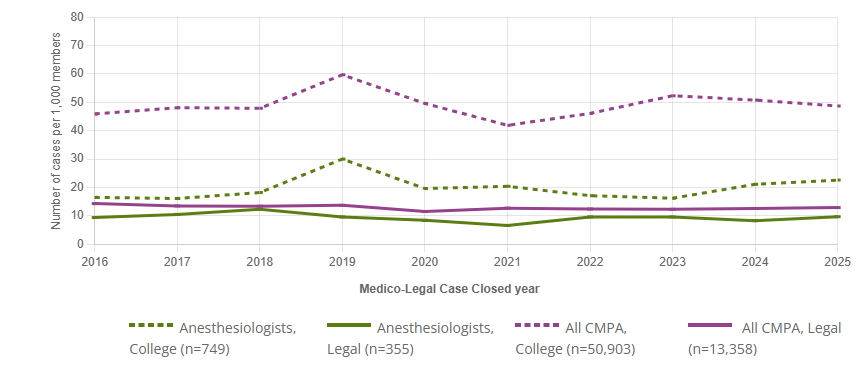
Between 2016 and 2025, anesthesiologists had significantly lower rates of College complaints (p<.0001) and civil legal actions (p<.0001) when compared to overall CMPA membership.1
What Are Your Risk Levels Regarding Medico-legal Cases, Compared to Other Anesthesiologists?
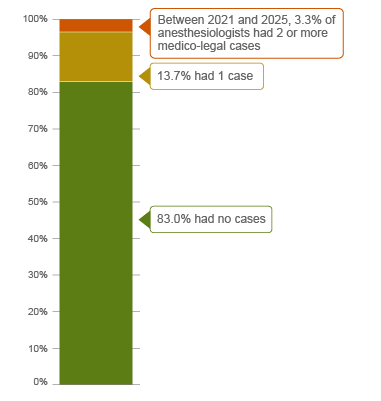
Percentage of Anesthesiologists, 5-Year Case Frequency
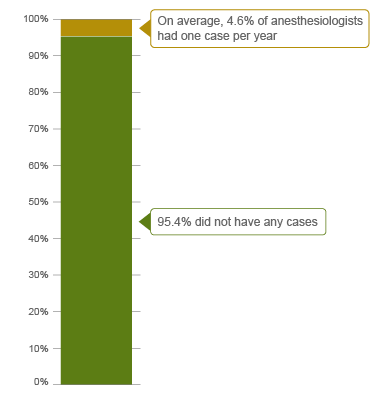
Percentage of Anesthesiologists, 1-Year Case Frequency
In a 5-year period (2021-2025),2 17% of all anesthesiologists were named in at least one case (including civil legal action, College, or hospital complaint).
Annually, over 95% of anesthesiologists did not have any cases, while the remaining 4.6% had an average of 1 case per year.
The following sections describe the findings based on the 600 civil legal cases College complaints, and hospital complaints involving anesthesiologists that were closed by the CMPA between 2016 and 2025.3
What Are the Most Common Patient Complaints and Peer Expert4 Criticism? (n=600)
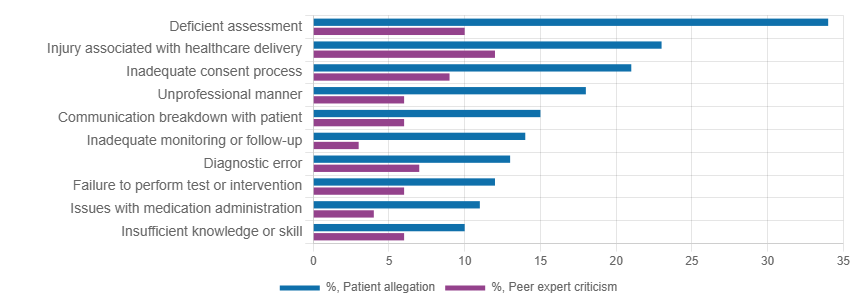
Complaints are driven by concerns of the patient or their family regarding issues that occurred during medical care. Patient complaints are not always supported by peer expert opinion. Peer experts may not be critical of the care provided or may have criticisms that are not part of the patient allegation. There may be more than one complaint or peer expert criticism in a case.
What Are the Most Frequent Interventions in Medico-legal Cases Involving Anesthesiologists? (n=600)
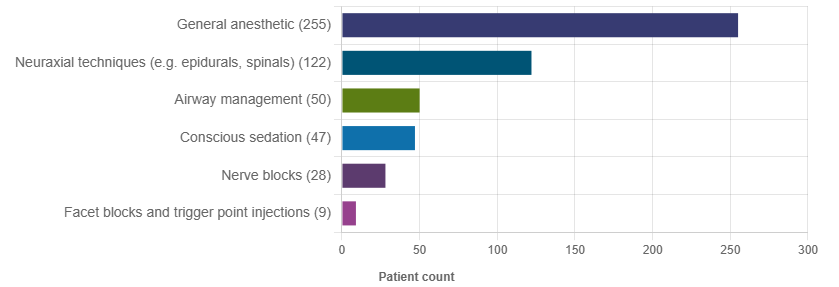
Intervention frequencies among medico-legal cases are likely representative of anesthesiologists’ practice patterns and do not necessarily reflect high-risk interventions.
The most common peer expert criticisms included:
- Inadequate documentation
- Deficient assessment
- Inadequate consent processes
- Communication breakdown with patient
Additionally, injury associated with healthcare delivery was a common issue for both patients complaints and peer expert criticism. For example:
- A patient incurred dental trauma during intubation; this risk was not described during the consent discussion or documentation.
- An anesthesiologist failed to adequately monitor and suction a patient’s airway intraoperatively, resulting in aspiration and the patient’s subsequent death to acute respiratory distress syndrome.
- A patient suffered an anoxic brain injury when an anesthesiologist was unable to intubate the patient after induction.
In addition, several cases involved diagnostic errors. For example:
- An anesthesiologist failed to consider an infectious cause of fever and new onset headache in a patient who underwent an epidural; the patient was subsequently diagnosed with meningitis.
- A patient developed paraplegia secondary to a delayed diagnosis of an epidural hematoma after receiving epidural anesthesia.
What Are the Top Factors Associated with Severe Patient Harm5 in Medico-legal Cases? (n=600)
Patient Factors6
Provider Factors7
- Deficient assessment (e.g. failure to adequately assess the patient’s cardiac history prior to anesthesia)
- Failure to perform test/intervention (e.g., failure to use ultrasound guidance for central line insertion)
- Inadequate consent process (e.g. failure to discuss infection as a possible risk of epidural)
- Deviation from clinical procedure (e.g. an incorrect medication being given via spinal injection when an anesthesiologist failed to follow medical safety protocols)
- Failure to attend (e.g. failure of on-call anesthesiologist to attend a deteriorating post-operative patient)
Team Factors8
- Communication breakdown with nursing staff
- Communication breakdown with another physician
Risk Reduction Reminders
The following risk management considerations have been identified for anesthesiologists, which reflect themes that emerged from peer expert review of CMPA cases.
Pre-Operative
- Obtain a detailed patient history, determine the appropriate model of anesthesia that aligns with the patient’s health goals, and discuss reasonable alternative options.
- Document all consent discussions, and decisions related to anesthesia care, including route/type of anesthesia and anesthetic procedures.
- Maintain an awareness of any relevant patient risk factors, including co-morbidities and history, that could have an impact on the patient’s management.
- During consent discussions for surgery or procedures, provide comprehensive information on material risks, benefits, alternatives, expected outcomes, and potential complications related to pre-existing conditions. Allow patients (and their family or caregivers, where appropriate) to ask questions. Thoroughly document the discussion in the medical record.
- Tailor your communication to meet the diverse needs of patients and their families while utilizing active listening techniques for clear and effective communication.
Intra-Operative
- When a procedure is difficult, or repeated attempts are unsuccessful, promptly consult a colleague for help.
- Provide the appropriate level of supervision of team members accounting for their level of experience.
- Review and verify the medication concentration, dosage, rate of administration, and route of administration before administering.
- Implement and follow standardized protocols to ensure interprofessional team situational awareness and improved verification practices (e.g., patient, site, and procedure).
Post-Operative
- Promptly disclose to patients (and families, where appropriate) any anesthesia complications that occurred perioperatively. Discuss the implications, anticipated postoperative course, and care plan. Ensure open communication and adequate follow-up. Document all discussions in the medical record.
- Communicate sufficient information, and invite input from all healthcare professionals, to promote situational awareness (i.e. keeping track of what is happening and anticipate what might need to be done) about patient condition and progress. Confirm that responsible team members appreciate the urgency of any concerns expressed about a patient’s condition or progress. Use standardized terminology in both verbal communication and when documenting patient status in the health record.
- Develop and implement team training and drills to enhance teams’ shared situational awareness, effective communication, and crisis response.
Limitations: The numbers provided are based on CMPA medico-legal data. CMPA medico-legal cases represent a small portion of patient safety incidents. Many factors influence a person’s decision to pursue a case or file a complaint, and these factors vary greatly by context. Thus, while medico-legal cases can be a rich source for important themes, they cannot be considered representative of patient safety incidents overall.
REFERENCES
1 Physicians voluntarily report College matters to the CMPA. Therefore, these cases do not represent a complete picture of all such cases in Canada.
2 It takes an average of 2-3 years for a patient safety incident to progress into a medico-legal case. As a result, newly opened cases may reflect incidents that occurred in previous years.
3 The concepts and themes discussed in this report are based on de-identified clinical summaries and expert opinions in medico-legal cases involving the relevant medical specialty.
4 Peer experts refer to physicians who interpret and provide their opinion on clinical, scientific or technical issues surrounding the care provided. They are typically of similar training and experience as the physicians whose care they are reviewing.
5 Patients who suffered severe harm or died. In CMPA Research glossary, severe patient harm is defined as symptomatic requiring life-saving intervention or major medical/surgical intervention, or resulting in a shortened life expectancy, or causing major permanent or temporary harm or loss of function.
6 Patient factors include any characteristics or medical conditions that apply to the patient at the time of the medical encounter, or any events that occur during the medical encounter.
7 The American Society of Anesthesiologists (ASA) Physical Status Classification System is used by physicians to predict a patient’s risks ahead of surgery. ASA status 3 indicates severe systemic disease.
8 Based on peer expert opinions.